
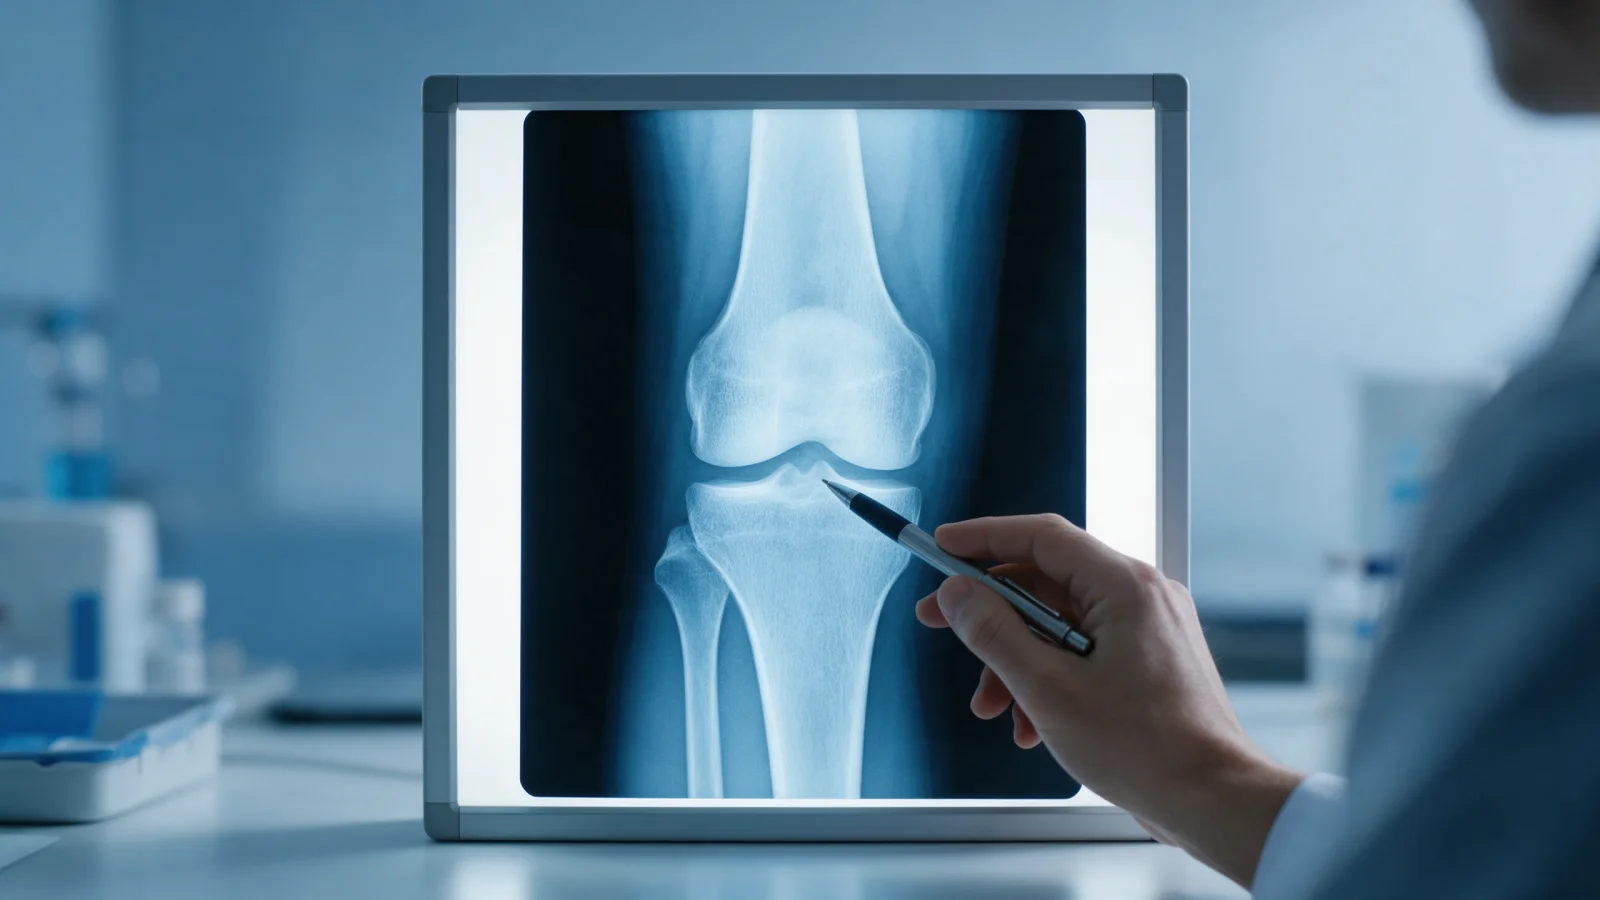
On a knee osteoarthritis X-ray, doctors look mainly for three findings: narrowing of the joint space, bony spurs at the joint edges (osteophytes) and hardening of the bone beneath the cartilage (sclerosis). These are most often graded from 0 to 4 using the Kellgren-Lawrence system. The grade alone does not decide treatment, though; that depends on symptoms, examination findings and the person's goals.
This article explains what osteoarthritis looks like on an X-ray, which views are taken, what each Kellgren-Lawrence grade means, how X-ray findings relate to pain and how the grade can influence treatment options.
What does knee osteoarthritis look like on an X-ray?
X-rays show bone; cartilage itself is not visible. In a healthy knee there is a clear gap between the thigh bone and shin bone, occupied by cartilage and the menisci. As osteoarthritis progresses the cartilage thins and this gap narrows, so joint space width gives an indirect picture of cartilage thickness. Typical findings include:
- Joint space narrowing: usually most obvious on the inner side of the knee, sometimes on the outer side or behind the kneecap.
- Osteophytes: bony spurs at the joint margins.
- Subchondral sclerosis: the bone just under the cartilage looks whiter and denser in response to increased load.
- Subchondral cysts: small round spaces within the bone.
- Deformity: in advanced cases, bow-legged or knock-kneed alignment becomes visible.
Which X-ray views are taken?
Ideally the X-rays are taken standing, with the knee bearing body weight, because lying-down films can make the joint space look wider than it is. Common views include a standing front view, a side view, a standing view with the knees slightly bent (which can reveal early narrowing better), a kneecap (skyline) view and, when planning osteotomy or replacement, a full-length leg X-ray to measure alignment. Which views you need is decided after examination. See our overview of imaging methods in orthopedics.
The Kellgren-Lawrence grades
- Grade 0: no X-ray signs of osteoarthritis.
- Grade 1 (doubtful): possible joint space narrowing and tiny, doubtful osteophytes.
- Grade 2 (mild): definite osteophytes, with possible mild narrowing.
- Grade 3 (moderate): multiple moderate osteophytes, definite narrowing, some sclerosis and possible change in bone-end shape.
- Grade 4 (severe): large osteophytes, marked narrowing or bone-on-bone contact, severe sclerosis and definite deformity.
Reports may write this as "KL 2" or "grade 3 osteoarthritis". Grade 2 and above is generally regarded as definite osteoarthritis on X-ray. For the early signs and symptoms, read our article on knee osteoarthritis.
Common phrases in X-ray reports
"Medial joint space narrowing" suggests cartilage thinning on the inner side of the knee; "marginal osteophytes" are bony spurs at the joint edges; "patellofemoral degenerative changes" refer to osteoarthritis behind the kneecap; and "varus alignment" means a bow-legged tendency that increases load on the inner compartment. None of these phrases alone is a diagnosis or a treatment decision; they need to be interpreted together with the examination.
Does the X-ray grade match the pain?
Not always. Some people with advanced changes on X-ray manage daily life with relatively little pain, while others with mild findings have marked symptoms. Pain is influenced by muscle strength, body weight, inflammation in the joint, bone marrow changes, meniscus problems and individual pain perception. That is why treatment is never decided on the X-ray report alone; the examination looks at range of motion, swelling, where the knee is tender, alignment and gait, and how much the symptoms limit daily life.
When is an MRI needed?
Osteoarthritis is usually diagnosed with examination and standing X-rays, so MRI is not needed for everyone. It may be requested if there is sudden pain not explained by the X-ray, catching or locking suggesting a meniscus tear, a suspected meniscus root tear or possible osteonecrosis, or to assess early cartilage damage when X-rays are still normal.
How does the grade affect treatment?
At every grade, non-surgical care is usually the foundation. The grade helps indicate which additional options may be discussed; treatment is always individual.
- Early grades (KL 1–2): exercise and strengthening, weight management, activity changes, physiotherapy and medication when needed; joint injections may be considered for some patients.
- Young, active patients with malalignment: when osteoarthritis is confined to one compartment, joint-preserving surgery such as high tibial osteotomy may be an option.
- Moderate (KL 3): non-surgical care continues; if symptoms persist, injections and, depending on the pattern, osteotomy or partial knee replacement may be considered.
- Severe (KL 4): if pain and stiffness significantly limit daily life despite non-surgical care, knee replacement may be discussed.
An advanced grade does not automatically mean surgery. People whose symptoms are well controlled may not need an operation, and with mild X-ray findings the symptoms may actually come from something else, such as a meniscus tear.
When should you see an orthopedic specialist?
- Knee pain lasting weeks and limiting daily activities
- Recurrent swelling or marked morning stiffness
- Catching, locking or giving way
- Increasing bowing or knock-knee deformity
- An X-ray report mentioning osteoarthritis that you are unsure how to interpret
Seek same-day care if the knee is red, hot and swollen with a fever, or if you cannot bear weight after a fall.
At Prof. Dr. Gökhan Polat's clinic, assessment combines examination, standing X-rays and further tests when needed, and treatment is planned around the grade together with age, activity level and personal expectations. Learn more on our knee joint diseases page.
In summary
- X-rays assess joint space narrowing, osteophytes and sclerosis; cartilage itself is not visible.
- The Kellgren-Lawrence system grades knee osteoarthritis from 0 to 4.
- The grade does not always match the level of pain; treatment depends on symptoms and examination too.
- Non-surgical care is the foundation at every grade; surgical options are considered individually.
This article is for general information only; diagnosis and treatment decisions are made individually after examination and the necessary tests.
Frequently asked questions
Does knee osteoarthritis show up on an X-ray?
Yes. Although cartilage is not visible on X-ray, signs such as joint space narrowing, osteophytes and bone sclerosis can be seen. Very early cartilage damage may not show, and MRI can be used if needed.
How many stages of knee osteoarthritis are there?
The widely used Kellgren-Lawrence system describes five grades, from 0 to 4, based on X-ray findings. Grade 0 means no signs, while grade 4 means marked joint space narrowing, large osteophytes and deformity.
Can grade 4 knee osteoarthritis be treated without surgery?
Even in advanced osteoarthritis, exercise, weight management, physiotherapy, medication and injections can be used to ease symptoms. If pain and stiffness still significantly limit daily life, knee replacement may be considered; the decision is individual.
Do I need an X-ray or an MRI for knee osteoarthritis?
An examination and standing X-rays are usually enough to diagnose knee osteoarthritis. An MRI may be requested if another problem such as a meniscus tear, root tear or osteonecrosis is suspected, or to look for early cartilage damage.
Does the X-ray grade show how bad the pain is?
Not always. Someone with advanced X-ray changes may have relatively little pain, while someone with mild findings may have significant pain. That is why treatment decisions consider symptoms and examination alongside the X-ray report.




