
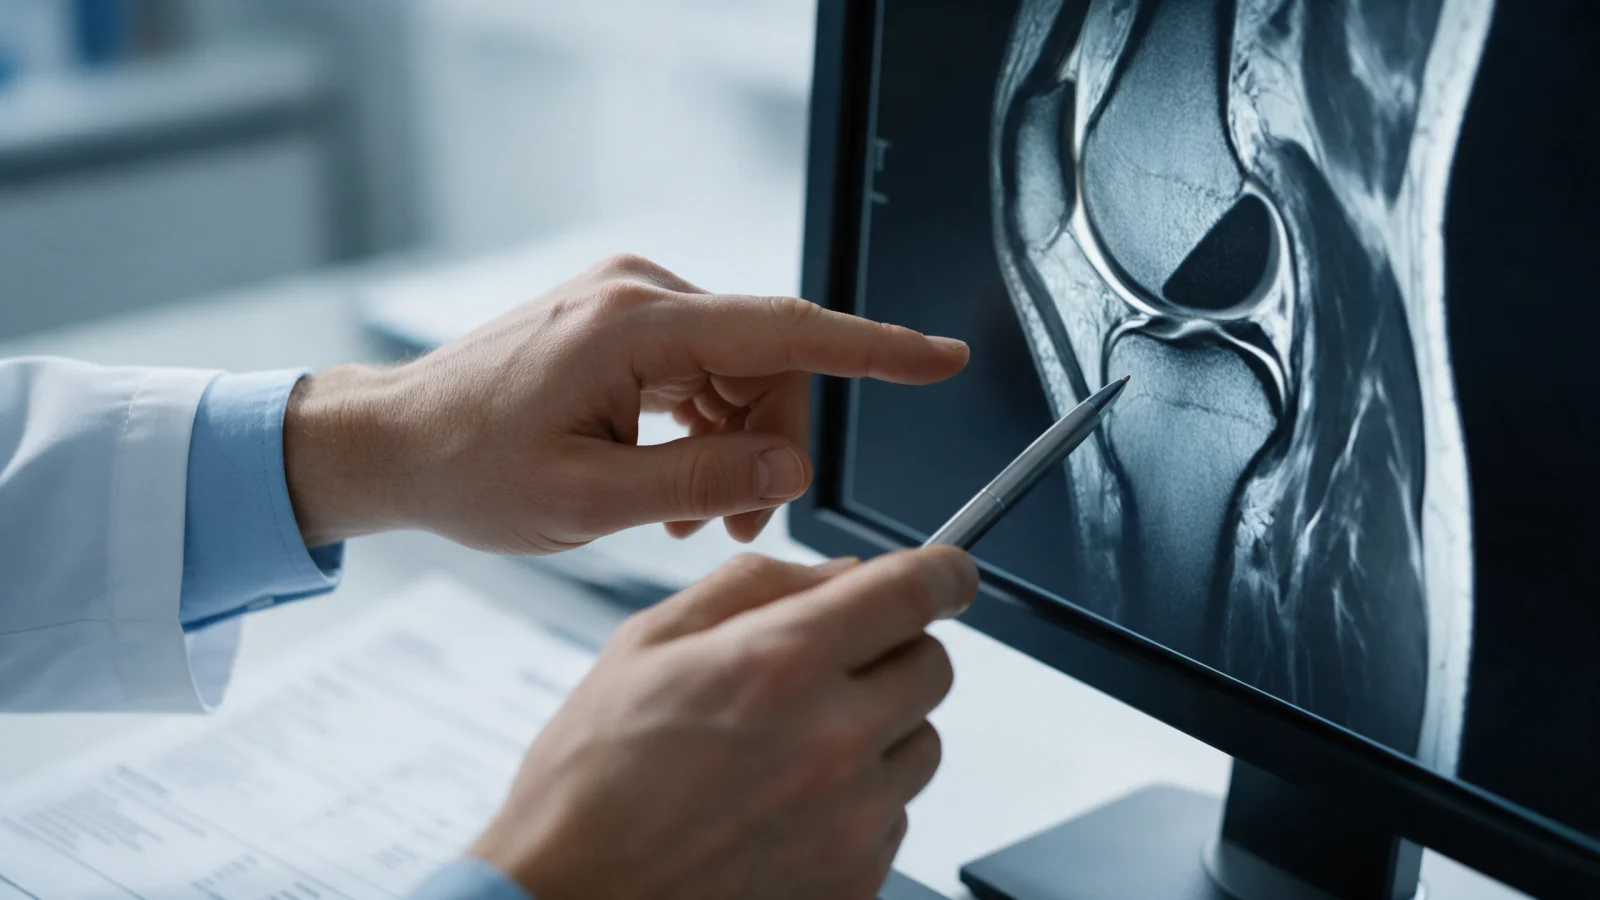
Reading a Meniscus MRI Report: Horizontal Tear, Posterior Horn
What do horizontal tear, posterior horn, signal change, radial and bucket-handle tear mean on a meniscus MRI report? A plain-language guide to reading your report and understanding treatment decisions.
On a meniscus MRI report, a "horizontal tear" is a tear that runs flat, splitting the meniscus into an upper and a lower layer; it is most often seen from middle age onwards as part of wear-related change. "Posterior horn" refers to the back part of the meniscus, which is the area that tears most often. These terms describe where a tear is and what shape it has, but on their own they do not say whether surgery is needed. Treatment decisions combine the MRI findings with your symptoms and examination.
This article explains, in plain language, the terms most often found on meniscus MRI reports: the parts of the meniscus, the difference between signal change and a tear, tear patterns, other findings that may appear, and what to ask once you have your report.
The meniscus and its parts
The menisci are two C-shaped cartilage cushions between the thigh bone and the shin bone. The one on the inner side of the knee is the medial meniscus, and the one on the outer side is the lateral meniscus. They spread load, stabilize the joint and protect the cartilage.
Radiology reports use these terms to describe location:
- Anterior horn: the front end of the meniscus.
- Body: the middle section.
- Posterior horn: the back end. The posterior horn of the medial meniscus takes the most load and tears most often.
- Root: where the meniscus attaches to bone. Root tears carry particular significance.
- Peripheral or red zone: the outer rim, which has a better blood supply, so tears here have more healing potential.
So "horizontal tear of the posterior horn of the medial meniscus" means a flat tear in the back part of the inner meniscus.
Signal change or tear? Understanding grades
A healthy meniscus appears on MRI as a smooth, dark triangle. When bright areas appear inside it, the report mentions "increased signal" or "signal change". What this means depends on whether the bright area reaches the surface of the meniscus:
- Signal that does not reach the surface (usually grade 1 or 2): wear within the meniscus, called degeneration. This is not a tear and becomes common with age.
- Signal that reaches the joint surface (usually grade 3): interpreted as a true tear.
The key point is that "degenerative signal change" on your report does not mean your meniscus is torn.
What do the tear patterns mean?
Horizontal tear
Runs parallel to the top of the shin bone and splits the meniscus into upper and lower leaves. It usually develops after the age of 40, often without a clear injury, on a background of wear. It can sometimes lead to a fluid-filled sac next to the meniscus (a parameniscal cyst). Many horizontal tears can be managed with physiotherapy and exercise.
Vertical or longitudinal tear
Runs along the length of the meniscus in a vertical plane. It typically occurs in young, active people after a twisting injury and may accompany an ACL tear. If it lies in the well-supplied outer rim, it may be suitable for repair.
Bucket-handle tear
A longitudinal tear whose inner fragment has flipped toward the center of the joint. It can cause locking or an inability to straighten the knee and usually needs prompt assessment.
Radial tear
Runs from the inner edge outwards, at right angles to the meniscus. It matters because it can seriously disrupt the meniscus's ability to carry load.
Oblique (flap) and complex tears
Oblique tears run at an angle and can create a loose flap that catches. "Complex" describes tears extending in more than one plane, usually in degenerative menisci.
Root tear
A tear at the point where the meniscus attaches to bone. Because it can largely disable the meniscus and speed up arthritis, it is considered separately. Read more in meniscus root tear: diagnosis, symptoms and treatment.
Other terms you may see
- Extrusion: the meniscus bulging out beyond the joint edge, which can be associated with a root tear or advanced degeneration.
- Effusion: extra fluid in the joint.
- Bone marrow edema: swelling within the bone, linked to injury, overload or arthritis.
- Chondromalacia or chondral defect: softening or thinning of cartilage.
- Baker's cyst: a fluid-filled sac behind the knee, often a sign of a problem inside the joint.
- Discoid meniscus: a meniscus that is wider and thicker than usual from birth, mostly on the lateral side.
Strengths and limits of MRI
MRI is very good at showing meniscus tears, but no test is flawless. Very small tears can be missed, scarring after previous meniscus surgery can mimic a new tear, and some signal changes are interpreted differently by different radiologists. Image quality also depends on the scanner, the technique and whether the patient can keep still. That is why an orthopedic surgeon looks at the images themselves, not just the report, and compares them with the examination. If the report and the examination do not match, further assessment or a period of follow-up may be suggested.
Does a tear on MRI mean surgery?
No. Meniscus tears are frequently found on MRI in middle-aged and older people who have no knee symptoms at all, so not every tear is the source of pain. Pain may also come from arthritis, cartilage damage or soft tissues around the knee, as discussed in can you have knee pain without a meniscus tear?
Key questions in deciding on treatment:
- Is the tear traumatic or degenerative?
- Are there mechanical symptoms such as locking, catching or inability to straighten the knee?
- Is the location and pattern suitable for repair?
- Is there an associated ligament injury or arthritis?
- What are the patient's age, activity level and goals?
In general, degenerative tears without mechanical symptoms are usually treated first with physiotherapy and exercise, while traumatic tears in younger patients, especially repairable ones, may lead to surgery sooner. For assessment and treatment options, see our meniscus tears page.
What to do after you receive your report
- Bring both the report and the images to your appointment; the surgeon will review the images too.
- Note when and how your symptoms started and which movements make them worse.
- Ask how the terms in the report relate to your symptoms.
- If surgery is suggested, ask whether repair or partial removal is planned, and why.
- Discuss whether non-surgical options are suitable for you.
When should you see an orthopedic surgeon?
- The knee locks in one position or will not straighten fully
- The knee gives way when walking
- Recurrent swelling
- Inability to bear weight
- Pain that has not improved after several weeks of exercise and activity changes
Sudden locking with an inability to straighten the knee may point to a displaced fragment and should be assessed without delay. At Prof. Dr. Gökhan Polat's clinic, MRI findings are interpreted together with the examination, and the treatment plan takes into account the tear pattern, age, activity level and the patient's goals. Response to treatment varies from person to person.
Summary
- "Posterior horn" is the back part of the meniscus; a "horizontal tear" splits the meniscus into two layers.
- Signal change that does not reach the surface means degeneration, not a tear.
- Tear pattern and location influence treatment, but not every tear seen on MRI causes pain.
- Diagnosis and treatment decisions come from combining MRI with the clinical examination.
This article is for general information only; diagnosis and treatment decisions are made individually after examination and the necessary tests.
FAQ
-
What does horizontal tear mean?
A horizontal tear runs flat, parallel to the top of the shin bone, splitting the meniscus into upper and lower layers. It mostly develops after the age of 40 on a background of wear, often without a clear injury. Many horizontal tears can be managed with physiotherapy and exercise.
-
What is a tear of the posterior horn of the medial meniscus?
It means there is a tear in the back part of the meniscus on the inner side of the knee. This area takes the most load and tears most often. Treatment is planned after examination, based on the tear pattern, symptoms, age and activity level.
-
Is increased signal in the meniscus a tear?
Not always. Signal that does not reach the surface of the meniscus usually indicates internal wear, called degeneration, and is not a tear. When the signal reaches the joint surface, it is interpreted as a tear.
-
If MRI shows a meniscus tear, do I need surgery?
No. Meniscus tears are often seen on MRI in people with no symptoms. Degenerative tears without mechanical symptoms such as locking are usually treated first with physiotherapy and exercise. The decision combines the MRI with your examination and symptoms.
-
What are the grades of meniscus tears?
MRI usually describes three grades: grades 1 and 2 are signal changes inside the meniscus that do not reach the surface and indicate degeneration, while grade 3 is a true tear reaching the joint surface. Grades alone do not determine treatment.